
KNEE CONDITIONS & TREATMENTS > ACL INJURIES
LEARN ABOUT YOUR KNEE
ACL Ruptures & Reconstruction
A (rather comprehensive) start to learning about ACL injuries.
Book a consultation with Dr Jon Liew to talk about your knee.
GENERAL INFORMATION
What are ligaments? What is the ACL?
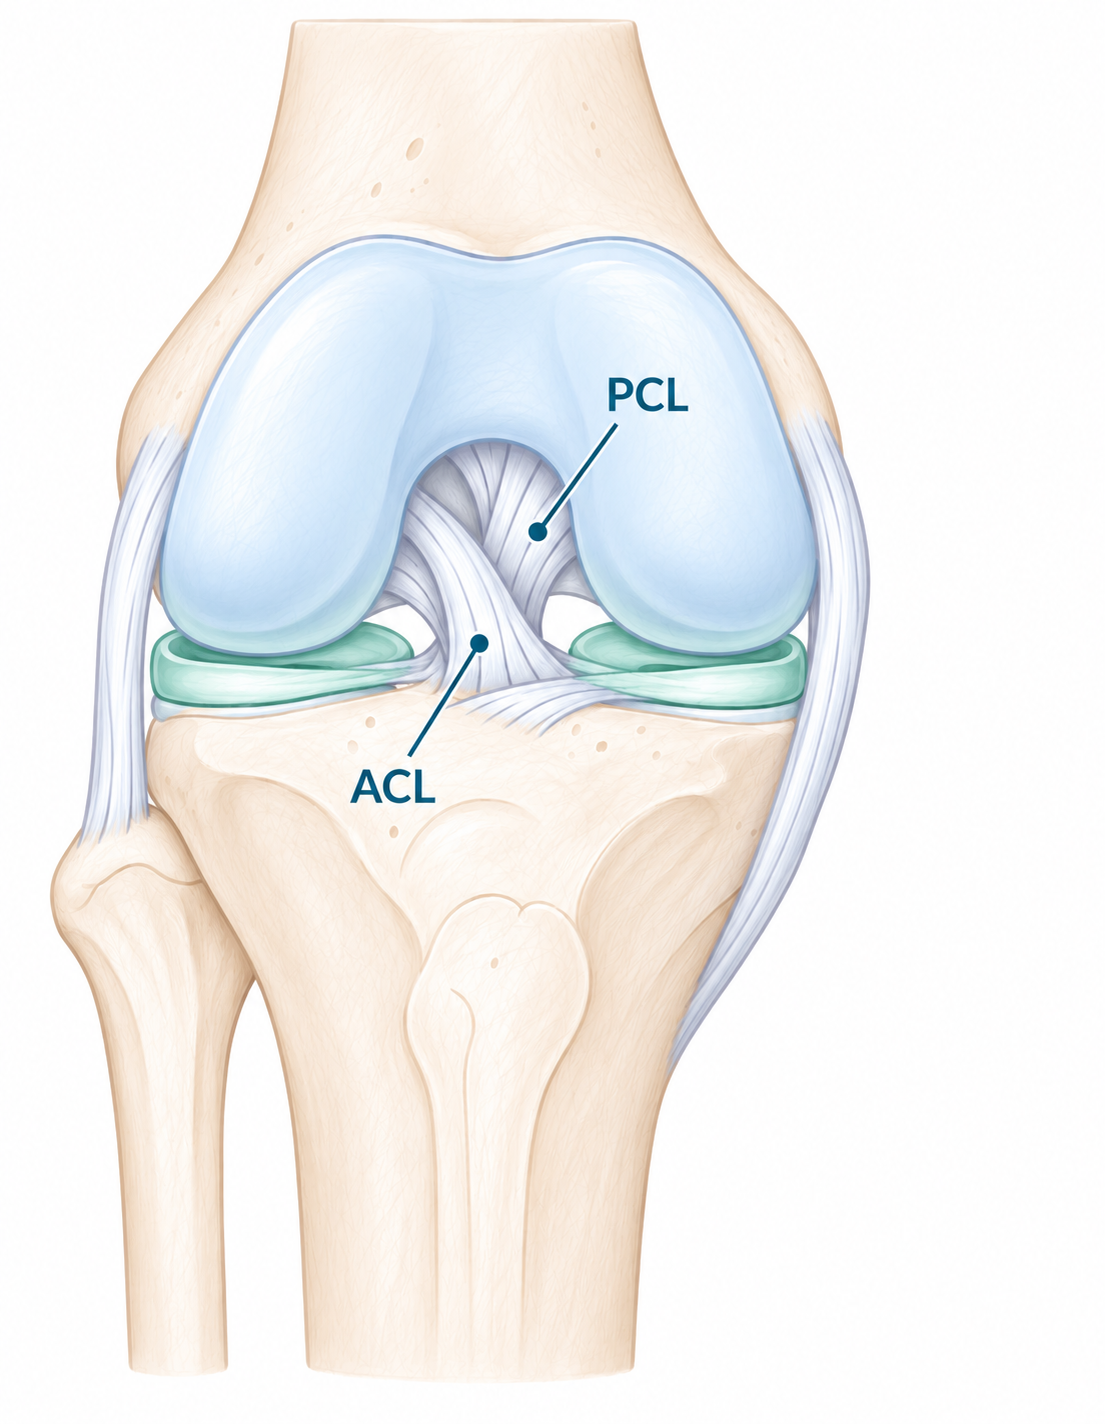
Ligaments are strong bands of tissue that connect bones to each other and help provide stability to a joint.
The anterior cruciate ligament (ACL) is one of the major ligaments of the knee, connecting the thighbone (femur) to the shinbone (tibia). ACL injuries are among the most common knee ligament injuries, particularly in sports involving pivoting, twisting and sudden changes of direction, such as soccer, Oztag, rugby, netball and basketball.
ACL injuries can range from partial tears to complete ruptures. Not all ACL injuries require surgery, and the most appropriate treatment depends on your individual circumstances. In selected patients, ACL reconstruction or repair may be recommended to restore knee stability and support a return to everyday activities and sport following rehabilitation.
SUPPORT GUIDE
I’ve torn my ACL!

Most commonly, you would have injured your ACL after a sudden change of direction, awkward landing or twisting movement. You may have felt or hear a “pop” in the knee, followed by immediate pain. Significant swelling within the first few hours is common. The knee may feel unstable, particularly when turning, pivoting or changing direction.
In the first week following the injury, pain and swelling may make it difficult to fully straighten or bend the knee.
It is also possible to injure other structures of the knee from the same incident - most commonly the meniscus or MCL. These can give additional symptoms such as clicking, locking or even more instability.
An assessment involves a detailed history and examination of the knee, supported by an MRI scan to assess the ACL and check for any of those associated injuries such as meniscal, cartilage or other ligament damage.
ACL RECONSTRUCTION AT A GLANCE
Operation
Arthroscopic (keyhole) ACL reconstruction using a tendon graft
Anaesthetic
Usually general anaesthetic, often with additional regional anaesthesia
Hospital stay
Usually same day or one night
Weight bearing
Usually immediately as tolerated unless associated injuries, with crutches initially
Knee brace
Not routinely required for isolated ACL reconstruction
Return to work
Desk work often 2 weeks; physical work usually earliest is 6 weeks
Return to running
Commonly around 3–4 months, depending on recovery
Return to sport
Usually 12 months for pivoting or contact sports, subject to rehab progress
Types of ACL injuries
ACL injuries can vary in their severity, location and pattern. Common types include:
Partial tears: Only some of the ACL fibres are torn, with part of the ligament remaining intact. The knee may still have some stability.
Complete ruptures: The ACL is completely torn, often resulting in significant knee instability, particularly during twisting or pivoting activities.
Avulsion injuries: Rather than tearing within the ligament itself, the ACL pulls away from its attachment to the bone, sometimes taking a small fragment of bone with it. These injuries are more common in children and adolescents.
Proximal and midsubstance tears: ACL tears can occur near the ligament's attachment to the femur or through its middle. The location and quality of the remaining tissue can influence whether the ligament may be suitable for repair or healing without surgery.
GENERAL INFORMATION
GENERAL INFORMATION
Common injuries associated with an ACL tear
ACL injuries frequently occur alongside damage to other structures in the knee. Some of the more common associated injuries include:
Meniscal tears
The menisci are two C-shaped structures that act as shock absorbers within the knee. Meniscal tears are common with ACL injuries and may cause clicking, catching or locking. Certain tears, such as displaced bucket-handle tears, may require more urgent surgery and are ideally repaired at the same time as an ACL reconstruction.
Medial collateral ligament (MCL) injuries
The MCL runs along the inner side of the knee and may be injured by the same twisting or sideways force that causes an ACL tear. Many MCL injuries can heal successfully with bracing and rehabilitation. My preference is usually to take a staged approach, allowing the MCL time to heal before reassessing knee stability and discussing the need for ACL reconstruction.
Cartilage and bone injuries
Damage to the smooth articular cartilage covering the joint surfaces can occur during an ACL injury. These injuries may contribute to ongoing symptoms and affect the long-term health of the knee.
Bone bruises are also commonly seen on MRI following an ACL rupture. They occur when the bones impact against each other during the injury and can contribute to pain and swelling.
Other ligament injuries
More significant injuries may also involve the posterior cruciate ligament (PCL), lateral collateral ligament (LCL) or posterolateral corner (PLC). These combined injuries can cause greater instability and may require more complex treatment.
GENERAL INFORMATION
Symptoms & Assessment
Common symptoms of an ACL injury include:
A popping sensation at the time of injury
Rapid knee swelling, pain and stiffness
Difficulty walking or bearing weight initially
A feeling of instability or the knee giving way
Difficulty twisting, pivoting or returning to sport
Pain and swelling often improve, but knee instability may persist, particularly during sports involving sudden changes of direction.
Your consultation will include a detailed history of your injury and an examination of knee movement, swelling and stability. Specific tests, including the Lachman and pivot-shift tests, help assess ACL function.
X-rays may be used to identify fractures or other bony injuries that can occur with an ACL rupture but do not visualise the actual ligament. An MRI scan is usually required to confirm the ACL tear and check for associated meniscal, cartilage or ligament injuries.
Non-surgical treatment
Not every ACL injury requires surgery. Some patients can return to normal activities and even certain sports with a structured rehabilitation program, particularly if their knee remains stable and they do not participate in high-demand pivoting sports.
Non-surgical treatment focuses on reducing swelling, restoring movement, strengthening the surrounding muscles, and improving balance and knee control through physiotherapy.
Can an ACL tear heal without surgery?
Traditionally, complete ACL tears were thought to have limited healing potential. However, recent research suggests that some ACL tears can demonstrate healing on MRI, although this does not always mean normal ligament function has been restored.
Newer bracing techniques, such as the Cross Bracing Protocol, aim to encourage healing by positioning the torn ligament ends closer together. Early research has shown promising results in selected patients, particularly when bracing begins soon after injury (ideally within 7–10 days). However, not all tears are suitable, and long-term outcomes remain uncertain.
The most appropriate treatment depends on the type of ACL tear, knee stability, activity demands and individual goals.
GENERAL INFORMATION
GENERAL INFORMATION
When is surgery recommended?
ACL reconstruction may be recommended if:
Your knee remains unstable despite rehabilitation
You wish to return to sports involving pivoting or sudden changes of direction
Your work requires a stable knee for physically demanding activities
You have associated meniscal or ligament injuries that may benefit from surgery
Not every complete ACL tear requires reconstruction. The decision is individualised and depends on your age, knee stability, activity level, associated injuries and personal goals.
Some patients with complete ACL tears function well without reconstruction, while others experience significant instability during relatively simple activities.
SURGERY
ACL reconstruction
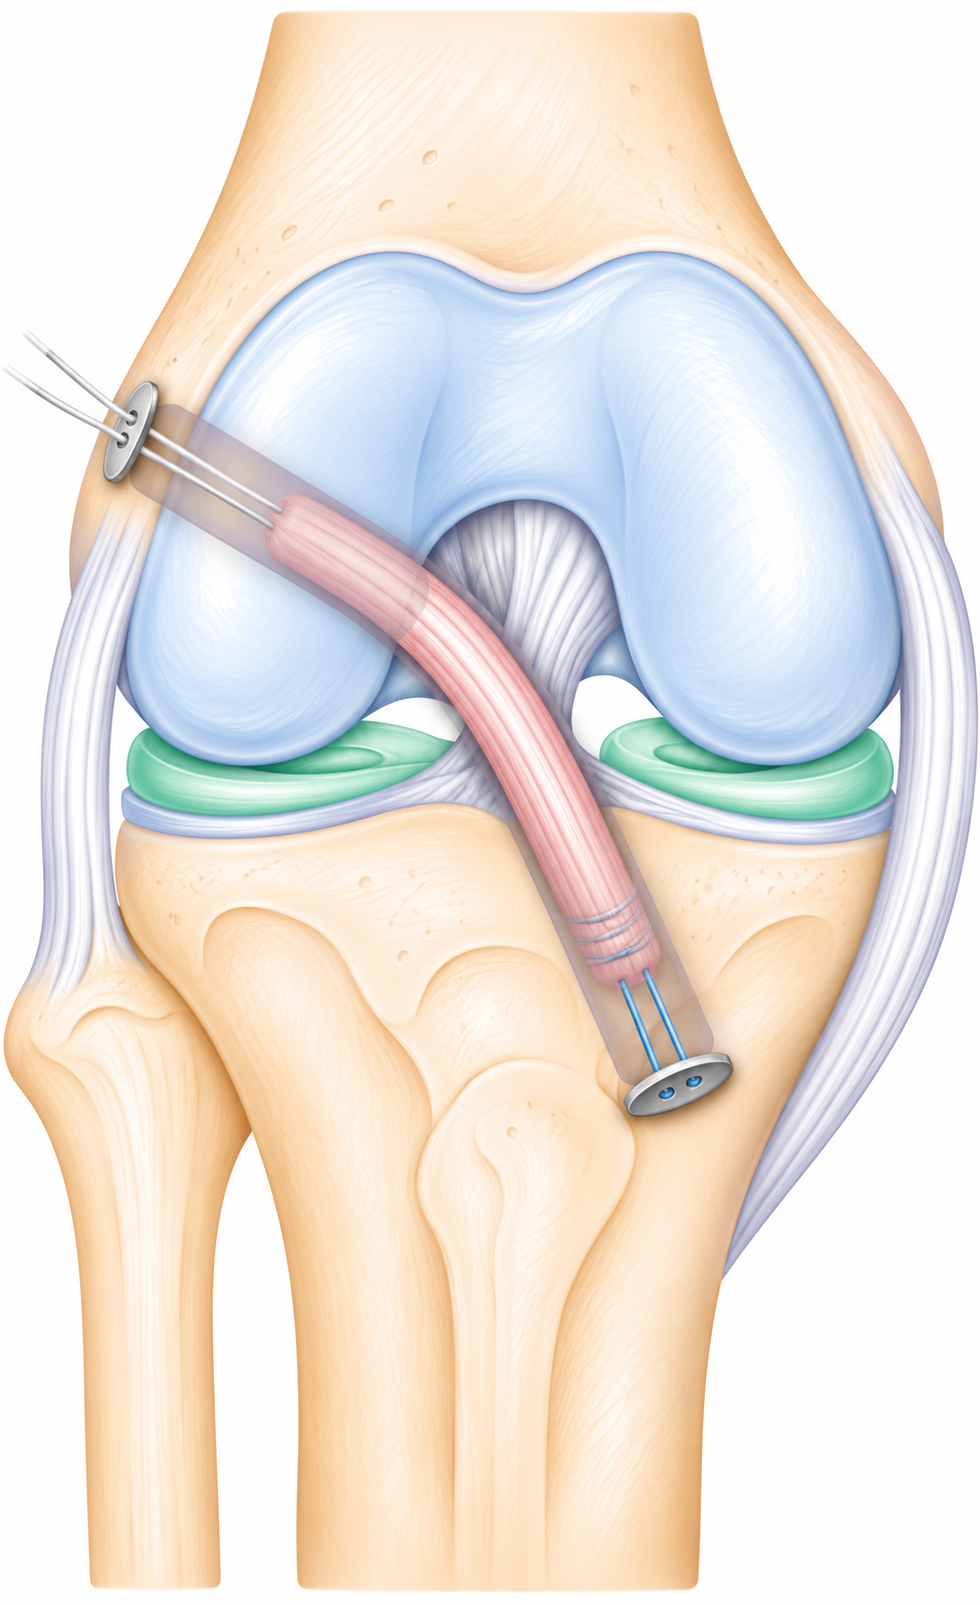
An arthroscopic ACL reconstruction is a keyhole operation that replaces the torn ligament with a tendon graft. The graft is positioned through small tunnels in the femur (thighbone) and tibia (shinbone) and secured using fixation devices such as buttons or screws. Associated meniscal or cartilage injuries may also be treated during the same operation. Graft options are discussed in more detail below.
Most patients return home on the same day or after one night in hospital.
What happens to the original ACL?
During an ACL reconstruction, the torn ligament is usually partially removed to allow clear visibility inside the knee and accurate positioning of the new graft. Damaged tissue that may interfere with knee movement is also removed, although some of the original ACL tissue may be preserved as it can actually be beneficial.
In selected injuries, repair of the original ACL may be possible instead of reconstruction. However, ACL reconstruction has historically provided more predictable outcomes. While newer repair techniques have shown promising results, particularly overseas, I currently favour reconstruction because of its more established long-term outcomes.
Lateral extra-articular tenodesis (LET)
In some patients, an additional procedure called a lateral extra-articular tenodesis (LET) may be recommended alongside ACL reconstruction to provide extra rotational stability and reduce the risk of the new ACL graft rupturing.
LET involves using a small strip of the iliotibial band (a strong band of tissue along the outside of the thigh) to reinforce the outer side of the knee and help control excessive twisting movements.
This procedure may be particularly beneficial for younger patients, those returning to pivoting sports, patients with significant rotational instability or those undergoing revision ACL reconstruction.
Not everyone requires an LET. The decision is individualised, balancing the potential benefits of additional stability against the risks of an extra procedure.
SURGERY
ACL graft choices
Several different tendon grafts can be used for ACL reconstruction, each with their own advantages and disadvantages.
A hamstring graft usually consists of the semitendinosus tendon, sometimes combined with the gracilis tendon, which are taken from the inner back part of the thigh through a small incision near the top of the tibia. It is a commonly used graft that avoids taking tissue from the knee's extensor mechanism (the quadriceps and patellar tendons). Potential disadvantages include a smaller graft if the tendons are naturally thin, some loss of hamstring strength and occasional hamstring cramping.
A quadriceps tendon graft is harvested from the tendon just above the kneecap. It provides a strong, substantial graft and has become an increasingly popular option for ACL reconstruction. This is my preferred graft option for most people returning to sport. Advantages include its reliable graft size and relatively low rates of anterior knee pain. Potential disadvantages include temporary quadriceps weakness, discomfort around the harvest site and an additional scar compared with a hamstring graft.
A bone–patellar tendon–bone (BTB) graft uses the central portion of the patellar tendon together with small blocks of bone from the patella and tibia. It provides secure bone-to-bone healing and has a long history of successful use, particularly in young athletes participating in high-demand sports. However, graft harvesting is relatively invasive, and potential disadvantages include anterior knee pain, discomfort when kneeling and, rarely, complications involving the patellar tendon or kneecap.
An allograft is donor tendon tissue obtained from another person. It avoids the need to harvest a tendon from the patient's own knee, but is generally associated with higher failure rates in younger, highly active patients. For this reason, allografts are usually reserved for selected circumstances where the risk of graft failure is lower.
So which graft is best?
There is no single graft that is best for everyone. Each option has its own benefits and potential drawbacks, and the most appropriate choice depends on your age, activity level, sporting goals and individual circumstances.
I will discuss the available options with you and recommend the graft that I believe offers the best balance of stability, long-term durability and recovery for your knee.
SURGERY
Recovery and rehabilitation
Rehabilitation is essential following ACL reconstruction, focusing on restoring knee movement, strength and stability while allowing the graft to heal.
Before surgery: Reduce swelling, restore movement and improve muscle strength.
0–6 weeks: Regain movement, muscle activation and normal walking.
6–12 weeks: Progress strengthening, balance and knee control.
3–6 months: Gradually introduce running, jumping and higher-level exercises.
9–12+ months: Return to pivoting and contact sports once strength, function and confidence have been restored.
Recovery is guided by your physiotherapist and individual progress, rather than time alone. Additional procedures, such as meniscal repair, may require modifications to rehabilitation.
Returning to sport too early increases the risk of re-injury.
Risks
ACL reconstructions are generally safe, but potential risks include:
Infection, bleeding or blood clots
Knee stiffness, persistent pain or swelling
Numbness or weakness around the graft harvest site
Graft failure or recurrent instability
Nerve or blood vessel injury (rare)
Anaesthetic complications or further surgery
Reconstruction does not eliminate the risk of re-injury or future osteoarthritis.
We will discuss these risks if you are considering surgery.
SURGERY
GENERAL INFORMATION
-
Yes, provided it is an isolated ACL tear. Many people can walk normally once the initial pain and swelling settle. However, the knee may still be unstable during twisting or sudden changes of direction.
-
Potentially. Repeated episodes of the knee giving way can cause further meniscal or cartilage damage. Activities should be modified according to your knee stability and symptoms.
-
A brace may be helpful in selected injuries, particularly when other ligaments are involved. However, routine bracing is not necessary for every ACL tear.
-
Provided there are no other injuries and you are not having episodes of instability, then an ACL reconstruction may not even be required and definitely can be safely delayed.
-
An isolated ACL reconstruction usually takes approximately 1–2 hours. Surgery may take longer if meniscal repairs or other procedures are required.
-
Unfortunately yes, pain and swelling are expected initially but generally improve over the first few weeks. Pain relief, icing, elevation and early rehabilitation help manage discomfort.
-
Yes. ACL reconstructions use small fixation devices to secure the graft. These are generally left in place permanently and rarely require removal. I usually use metal buttons, but for some grafts will use screws.
-
This would be a disappointing outcome. We would consider and discuss an further operation, known as revision ACL reconstruction. This depends on knee stability, associated injuries, previous graft choice and your activity goals.
-
Yes, I routinely repeat an MRI at 12 months after the surgery to assess the graft. We can repeat an MRI sooner if there are any concerns.
-
Many patients regain excellent knee strength and stability following reconstruction and rehabilitation. However, recovery varies, and returning to your previous level of sport depends on strength, confidence and associated injuries. According to research, most patients do not achieve the same strength as their non-injured leg.
-
An ACL injury increases the risk of developing knee osteoarthritis, particularly when associated with meniscal or cartilage damage. Reconstruction improves stability but does not necessarily prevent arthritis.
-
Yes. Children and adolescents can undergo ACL reconstruction, but I may need to use special techniques to protect their developing growth plates. Treatment is tailored to the child's age, skeletal maturity and activity level.
Frequently Asked Questions (FAQ)
HOW I CAN HELP
Surgical procedures I offer for ligament injuries, when clinically appropriate:
ACL Reconstruction utilising several potential graft options: Autograft (Quadriceps, Hamstring, Patella tendon) or Allograft
Paediatric ACL Reconstruction (with ITB)
Extra-articular Lateral Tenodesis
PCL Reconstruction
MCL Reconstruction
Posterolateral corner / LCL Reconstruction

CONTACT US
Make some time for you and your knee
Dr Jon Liew consults at the San Clinic (Wahroonga) on Sydney’s Upper North Shore.
